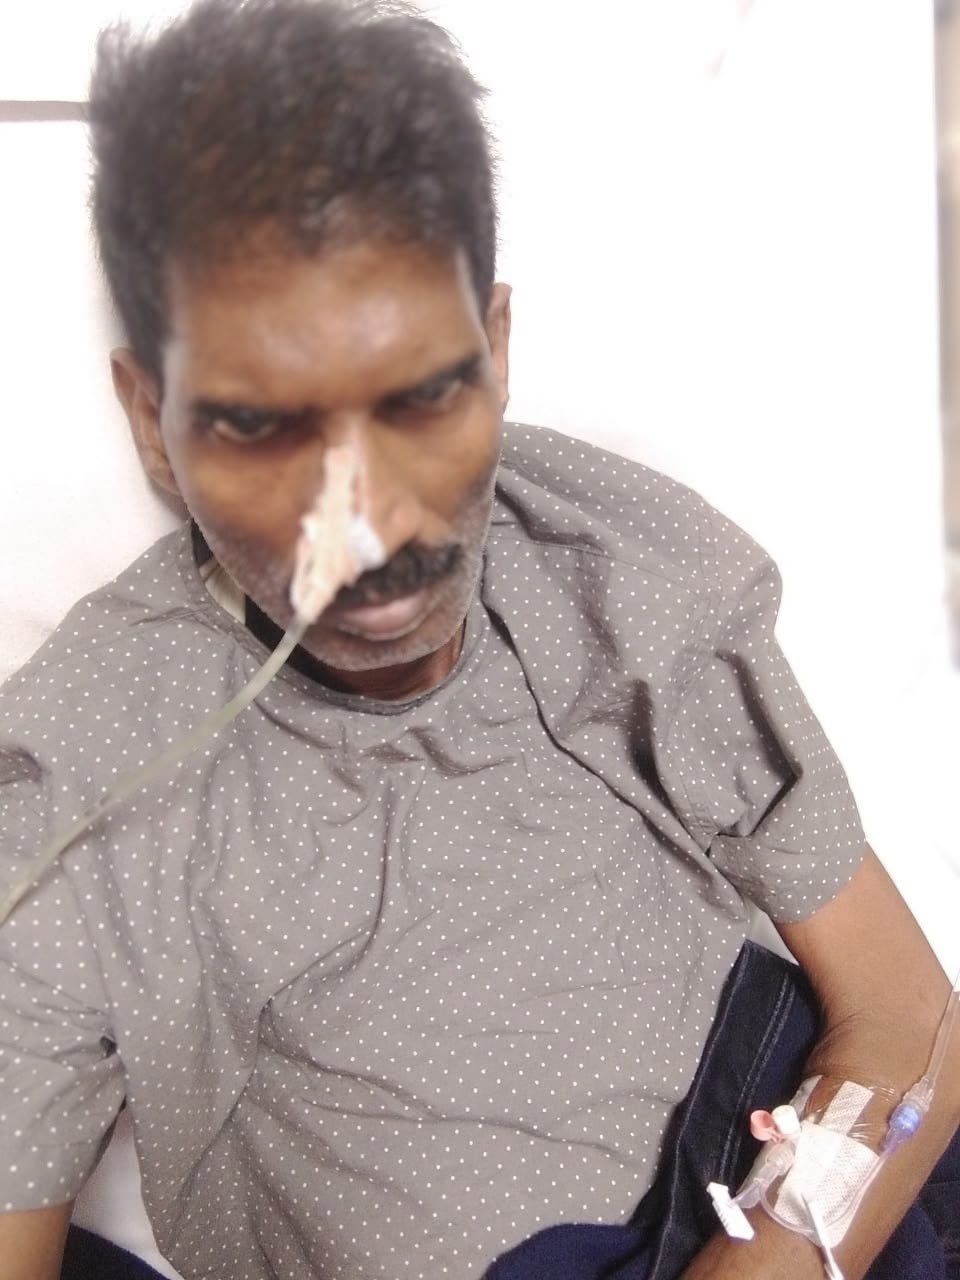
G. Prasad, 49, is battling advanced Crohn's disease with severe intestinal strictures. He cannot eat and has lost significant weight. Doctors have recommended an urgent exploratory laparotomy. His family cannot bear this cost alone.
Or Scan QR Code to Pay
pallaviprasad0416@okaxis
Scan with any UPI app to pay
G. Prasad, 49, was first diagnosed with Crohn's disease in 2018. After years of managing with medication, his condition has worsened significantly. He is now unable to tolerate solid food — every attempt to eat causes severe cramping abdominal pain around his navel.
The inability to eat has caused rapid, significant weight loss and extreme weakness. CT imaging reveals multiple intestinal strictures, active inflammation, and a high-grade partial small bowel obstruction involving the distal jejunum and proximal ileum.
During his September 2026 hospitalization at AIG Hospitals, Banjara Hills, the surgical gastroenterology team explained the critical need for surgery. Doctors have planned a diagnostic laparoscopy and bowel resection — with or without a stoma, depending on what is found during surgery.
The follow-up note from AIG Hospitals states clearly: "Urgent hospitalization required. Plan exploratory laparotomy and proceed." Time is critical.
Dr. Partha Pal — Director, IBD Centre · Medical Gastroenterology
Dr. Pradeep Rebala — Consultant Surgical Gastroenterologist
2018 — Crohn's disease diagnosed
Feb 2026 — Colonoscopy & biopsy at AIG
Mar 2026 — CT confirms strictures
Sep 1, 2026 — Admitted with obstruction
Sep 2, 2026 — CECT confirms high-grade obstruction
Sep 3, 2026 — Discharged DAMA; surgery funds needed urgently
The following is AIG Hospitals' initial pre-admission estimate (Estimate No. ESTB1862). Final costs may be higher based on actual treatment, investigations, and any additional medical needs.
| Item | Amount (INR) |
|---|---|
| Room Rent — Sharing (5 days × ₹4,950) | ₹24,750 |
| Surgeon Fee (Dr. Pradeep Rebala) | ₹1,70,000 |
| Investigation Charges | As per actual |
| Drug Charges | ₹1,50,000 |
| Consumable Charges | ₹20,000 |
| Admission Charges | ₹1,200 |
| ICU Charges (2 days × ₹12,000) | ₹24,000 |
| Miscellaneous | ₹30,000 |
| Initial Estimate Total | ₹4,19,950 |
⚠ Blood tests, blood requirements, and other complications are additional. The fundraising goal of ₹5,50,000 covers these additional expenses. Minimum deposit required at admission: ₹3,20,000.
Planned laparoscopy and bowel resection with or without stoma
Room charges, nursing care, and facility fees for 7+ days
IV antibiotics, drugs, and post-operative consumables
Transfusions and blood products if needed during surgery
Post-surgical intensive care monitoring for at least 2 days
Lab work, imaging, and additional tests as clinically required
All medical records and hospital documents are available for your review. We believe in full transparency.
Even a small gift brings G. Prasad closer to the surgery he urgently needs. Share with your network if you can't donate — it costs nothing and saves a life.
Or Scan QR Code
pallaviprasad0416@okaxis
Scan with any UPI app · Google Pay, PhonePe, Paytm
Payments go directly to Pallavi Geddada (daughter of G. Prasad) via UPI. For queries, please reach out through the contact on the fundraiser poster. Please keep G. Prasad in your prayers. 🙏
AIG Hospitals Surgery Estimation
Estimate No. ESTB1862 · Dated 18/09/2026 · Patient UHID: AIGG.21293071
Surgeon: Dr. Pradeep Rebala · Minimum Deposit: ₹3,20,000
| Item | Amount (INR) |
|---|---|
| Room Rent — Sharing (5×₹4,950) | ₹24,750 |
| Surgeon Fee | ₹1,70,000 |
| Investigation Charges | As per actual |
| Drug Charges | ₹1,50,000 |
| Consumable Charges | ₹20,000 |
| Admission Charges | ₹1,200 |
| ICU Charge (2 days) | ₹24,000 |
| Miscellaneous | ₹30,000 |
| Total Amount | ₹4,19,950 |
LAMA Summary (Left Against Medical Advice)
UHID: AIGG.21293071 · IP No: 4003258 · Admission: 01-09-2026 · Discharge: 03-09-2026
Primary: Dr. Partha Pal (Director, IBD Centre) · Referral: Dr. Pradeep Rebala
• Crohn's Disease — A3 L3+L4 B2+B3
• Subacute Intestinal Obstruction (Stricture at Distal Jejunum and Proximal Ileum)
Patient presented with increasing abdominal pain for 3–4 weeks, abdominal distension from 2 months — increased with food/fluid intake. No fever, vomiting, hematemesis, or blood in stool. Previously diagnosed with Crohn's in 2018 and treated with Mesacol twice daily. CT enterography done 03/03/2026. Started on Wysolone 20 mg once daily 20 days prior to admission.
Known Crohn's disease with active stricturing disease involving the distal jejunum and proximal ileum, causing moderate to severe luminal narrowing and resultant upstream small-bowel dilatation with distal bowel collapse — consistent with high grade partial small bowel obstruction. Associated mild penetrating disease adjacent to the ileal lesion. No associated abscess.
CECT Abdomen Report
Bill Date: 02-Sep-2026 · Reporting Date: 03/09/2026 12:32PM · Accession No: 1I.2082634.33749
Ref. Phys: Dr. Partha Pal · Approved by: Dr. Chaithanya Isamalla, MBBS MDRD, Director Sr. Consultant Radiology
"Known Crohn's disease with active stricturing disease involving the distal jejunum and proximal ileum, causing moderate to severe luminal narrowing and resultant upstream small-bowel dilatation with distal bowel collapse — consistent with high grade partial small bowel obstruction. Associated mild penetrating disease adjacent to the ileal lesion in the right hypochondrium with heterogeneously enhancing incomplete sinus tracts. No associated abscess. Persistent mild mucosal enhancement of the cecum and proximal appendix — residual inflammatory change. Mildly enlarged jejunal mesenteric lymphnodes — likely reactive."
• Proximal ileum stricture (right hypochondrium): 2.8 cm length, max wall thickness 12mm, moderate to severe luminal narrowing
• Distal jejunum stricture: ~4.5 cm length, max wall thickness 9.8mm
• Upstream small bowel dilatation (max luminal diameter 6.5 cm in proximal jejunum)
• Incomplete sinus tracts — no abscess
• Jejunal mesenteric node: 11.8 mm · Ileal mesenteric node: 5.6 mm (reactive)
• Multiple enteroliths in mid-dilated jejunal loops
• Osteopenia of pelvic bones
• Liver, kidneys, spleen, pancreas, aorta — normal
Laboratory Investigation Reports
AIG Hospitals, Banjara Hills · Ref. Dr. Partha Pal · Verified by: Dr. G. Deepika (Dir. HOD Biochemistry)
| Test | Result | Reference Range | Date |
|---|---|---|---|
| Renal Function Tests (Urea, Creat, Elect) — 03/09/2026 | |||
| Blood Urea | 24 mg/dL | 16.6–48.5 | 03/09 |
| Serum Creatinine | 0.97 mg/dL | 0.7–1.2 | 03/09 |
| Sodium | 134 mEq/L ▼ | 136–145 | 03/09 |
| Potassium | 4.9 mEq/L | 3.5–5.1 | 03/09 |
| Chloride | 100 mEq/L | 98–107 | 03/09 |
| Serum Electrolytes — 01/09/2026 | |||
| Sodium | 132 mEq/L ▼ | 136–145 | 01/09 |
| Potassium | 4.9 mEq/L | 3.5–5.1 | 01/09 |
| Chloride | 98 mEq/L | 98–107 | 01/09 |
Discharge Summary & Medications
Discharge Date: 03-09-2026 08:02 PM (DAMA — Discharged Against Medical Advice)
Patient was discharged at attendees' request after being explained the need for surgery
Temp: 98.6 · Pulse: 84 · BP: 102/73 · SpO2: 99%
Patient was conscious/coherent. Treated with IV fluids, IV antibiotics (Zostum, Metrogyl), nasogastric tube insertion. 350 mL RT output noted (suspected food). Surgical opinion sought and advice followed.
1. Sompraz IT Cap (Esomeprazole 40mg + Itopride 150mg) — Once daily before breakfast · 1 month
2. Bevon 200mL Syrup (Multivitamine) — Twice daily after food · 1 month
3. Drotin 40mg Tab (Drotaverine) — SOS (as needed)
Diet: Exclusive enteral nutrition as advised by dietitian.
Follow-up: Urgent hospitalization required. Plan exploratory laparotomy and proceed.
Review SOS in Medical Gastroenterology OPD.